Wet AMD Injections: The Treat-and-Extend Approach
How anti-VEGF injections work for wet age-related macular degeneration, how the treat-and-extend schedule differs from monthly dosing, and what follow-up involves — based on the 2021 Chinese expert consensus on aflibercept treat-and-extend for neovascular AMD.
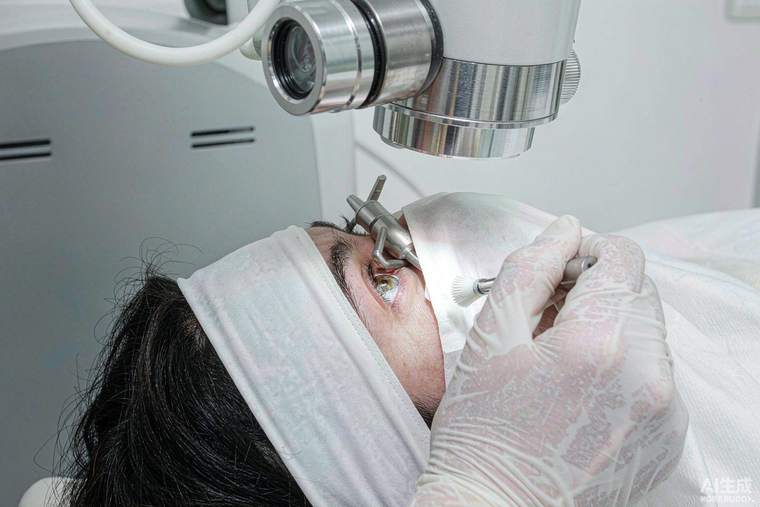
Neovascular (wet) age-related macular degeneration happens when abnormal blood vessels grow under the central retina and leak fluid or blood, distorting and destroying central vision. Anti-VEGF injections into the eye — blocking the signal that drives those vessels — transformed a condition that once caused inevitable central blindness into one where most patients retain useful reading and recognising vision. The challenge is not whether to inject but how often: indefinite monthly injections are burdensome for patients and clinics, while under-treating allows fluid to return and vision to be lost permanently. The 2021 Chinese expert consensus addresses the treat-and-extend regimen with aflibercept.
How anti-VEGF treatment works
The drug is injected into the vitreous with a very fine needle under topical anaesthesia after antiseptic preparation; the procedure takes minutes and is repeated at intervals indefinitely in most cases. Aflibercept, ranibizumab, conbercept and bevacizumab are all used; aflibercept binds VEGF-A, VEGF-B and placental growth factor and has a relatively long duration of action, which is one reason it suits extended intervals. The aim of every visit is a retina free of fluid on optical coherence tomography — the OCT scan, not the symptom, is what guides retreatment.
What treat-and-extend means
Instead of a fixed monthly or fixed bimonthly schedule, treat-and-extend individualises the interval: injections start at regular intervals, and if the retina is dry, each subsequent interval is lengthened — by two weeks at a time, commonly up to twelve or sixteen weeks; if fluid reappears, the interval is shortened by two weeks and the new, shorter interval becomes the maintenance interval. Compared with fixed dosing, this approach maintains vision with substantially fewer injections and visits, which reduces cost, travel burden and the cumulative risk of repeated injections, while compared with purely reactive "treat only when fluid appears" regimes, it avoids the cycles of fluid accumulation that are associated with permanent vision loss and scarring.
Monitoring and expectations
Each visit typically includes visual acuity measurement, OCT and, where indicated, fluorescein angiography or indocyanine green angiography to characterise the lesion. Patients are asked to report new distortion, a new dark patch or a sudden drop in vision between visits, because delaying treatment when fluid returns is where vision is lost. Home monitoring with an Amsler grid, or with a preferential hyperacuity or smartphone-based test where available, helps detect change early.
Safety and practicalities
Anti-VEGF injections are very safe overall but not risk-free. Serious complications are uncommon — infection inside the eye (endophthalmitis) in roughly one in a thousand or fewer injections, retinal detachment, cataract progression and sustained pressure rises; transient floaters, a gritty eye and subconjunctival bleeding are common and benign. The systemic safety profile is reassuring, though the decision is individualised in patients with recent stroke or thromboembolic disease. Both eyes can be treated on the same day when both are affected.
Practical guidance
Expect treatment to be long-term, and plan around it: injections are usually given in a clean procedure room, not an operating theatre, and most patients are in and out within an hour. Ask what your current interval is, what the target interval is, and what finding would shorten it. Keep every appointment even when vision feels stable — the point of monitoring is to detect fluid before vision changes. And ask about the non-injection half of the plan: smoking cessation, blood pressure control, dietary lutein and antioxidant intake, and low-vision support all contribute to preserving the vision you have.