Brain Haemorrhage on Blood Thinners: Emergency Reversal and Aftercare
Why bleeding into the brain while on anticoagulants or antiplatelets is different, how clotting is reversed, when surgery is considered, and when to restart the blood thinner — based on the Chinese multidisciplinary guideline on coagulopathy-related intracerebral haemorrhage.
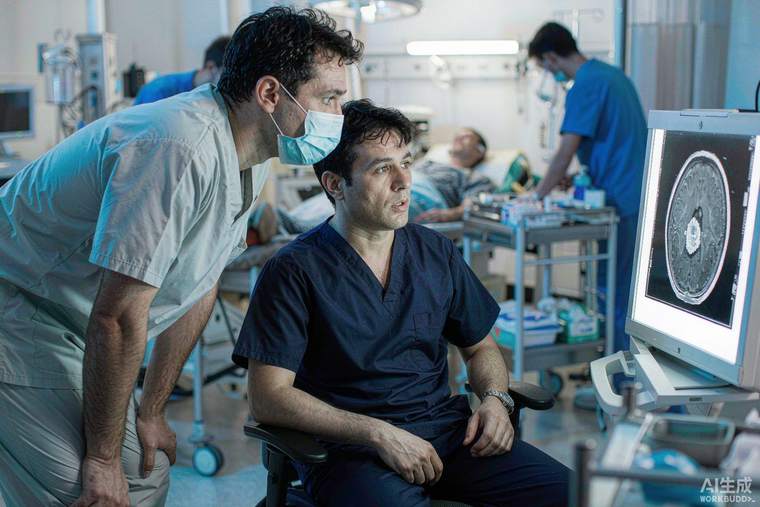
Intracerebral haemorrhage in a patient taking anticoagulant or antiplatelet medicines — or with an underlying bleeding disorder — behaves differently from ordinary hypertensive bleeding: haematomas expand more often, outcomes are worse and mortality is higher. Oral anticoagulant-related bleeding accounts for roughly a quarter of all spontaneous brain haemorrhages in reported series. Management therefore hinges on reversing the clotting defect as fast as possible, and on the difficult subsequent decision of whether and when to restart the blood thinner. This guide follows the Chinese multidisciplinary guideline on coagulopathy-related intracerebral haemorrhage.
The first hours
Pre-hospital, the priorities are recognising a possible stroke, protecting the airway, and — if the patient takes anticoagulants or antiplatelets — stopping the drug immediately and alerting the receiving hospital so the stroke pathway can prepare reversal agents. In the emergency department, a rapid assessment of vital signs is followed by a focused history: exactly which drug, the last dose, whether doses were missed, any personal or family bleeding history, and any other medicines — including over-the-counter aspirin, NSAIDs and supplements — or toxin exposures. Blood tests include a full blood count, kidney and liver function, PT/INR, APTT, thrombin time and fibrinogen, with viscoelastic testing such as thrombelastography where available. A head CT is obtained urgently and repeated if the patient deteriorates.
Reversal
Treatment is specific to the drug. Vitamin K antagonist (warfarin) bleeding is reversed with intravenous vitamin K plus four-factor prothrombin complex concentrate, which normalises INR quickly and limits haematoma expansion better than fresh frozen plasma. Direct oral anticoagulants are reversed agent-specifically: idarucizumab for dabigatran, and andexanet alfa or four-factor PCC for factor Xa inhibitors. Heparin is reversed with protamine; antiplatelet agents have no specific antidote, and the role of platelet transfusion is individualised and generally avoided in patients on antiplatelets without a surgical indication. Coagulation factor replacement is used for haemophilia and other factor deficiencies, and specific treatments for rare bleeding disorders.
Surgery and monitoring
Indications for surgery follow general brain-haemorrhage principles — deteriorating consciousness, large superficial clots, posterior fossa haemorrhage, hydrocephalus, or a resectable underlying lesion such as an aneurysm or tumour — but surgery in these patients requires particular attention to haemostasis, and outcomes are better when reversal precedes the operation. Monitoring in a high-dependency setting includes repeated neurological assessment, repeat imaging to detect expansion, blood pressure control to a defined target, and management of intracranial pressure.
The restart decision
Every patient on a blood thinner for atrial fibrillation, a mechanical valve or prior thrombosis faces a balancing act: restarting risks haematoma expansion, while staying off it risks a clot — stroke, pulmonary embolism or valve thrombosis. The guideline frames this as an individualised, timed decision based on the indication for anticoagulation, haematoma size and stability, blood pressure control, and the patient's own values. Antiplatelets for secondary prevention are generally resumed earlier than therapeutic anticoagulation; where the thrombosis risk is very high, earlier resumption or a different strategy such as left atrial appendage closure may be considered.
What families can do
Keep a written, current list of every blood thinner and antiplatelet, with dose and last intake, and carry it. Know the reversal plan exists and ask whether your hospital stocks the specific agent. After the acute phase, ask three questions: why was I on this medicine, what is my bleeding risk versus my clotting risk, and what is the plan and the date for restarting?