In short
Chronic constipation affects about 15 percent of adults. The modern approach separates slow-transit from outlet obstruction, starts with fibre and osmotic laxatives, and moves to physiological testing and pelvic floor therapy when those fail.
What this guide covers: History and examination · Sorting out the subtype · First-line treatment · When first-line treatment fails · Specific therapies for pelvic floor dysfunction
Chronic constipation is one of the commonest reasons for a gastroenterology or colorectal surgery consultation, affecting roughly 15 percent of the population. It is not a single disease. It divides into normal-transit constipation, slow-transit constipation and outlet obstruction — often called defaecatory disorder — and the treatment differs substantially between them, which is why the assessment matters more than the prescription.
The current clinical practice approach, reflected in the American Society of Colon and Rectal Surgeons guideline and widely adopted, is a stepwise one.
History and examination
The first job is to exclude something else. History and examination aim to identify features of concern: rectal bleeding, narrowing of stool, weight loss, anaemia, or a family history of colorectal cancer. Any of these warrants endoscopic evaluation rather than empirical laxatives.
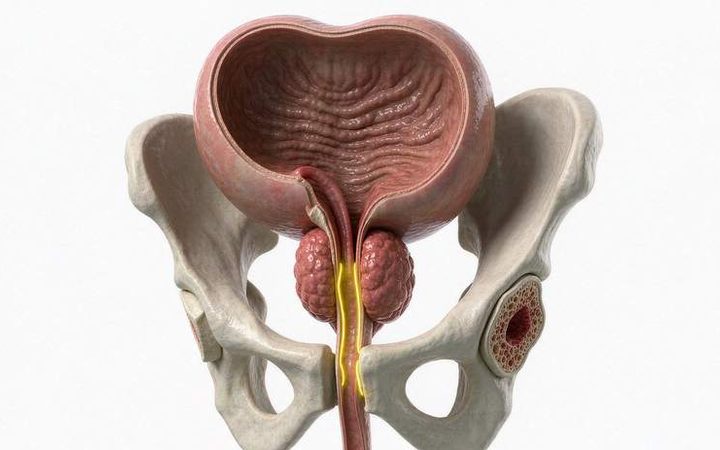
Examination includes the abdomen — usually non-tender, sometimes distended, and any palpable mass should be noted — and the anorectal examination. Digital rectal examination can identify high anal tone, paradoxical contraction of the puborectalis, a rectocele, a mass, a stricture or impaction. Asking the patient to bear down while examining reveals how much the pelvic floor descends and whether the muscles relax as they should.
Two further questions are routinely asked. Which medicines is the patient taking — opioids, antidepressants, anticholinergics, calcium channel blockers and calcium supplements are all common contributors? And are there behavioural contributors — low fluid intake, low fibre, and inactivity?
Sorting out the subtype
The pattern of symptoms points to the mechanism. Infrequent passage of hard stool suggests disordered colonic transit. A sense of incomplete evacuation and straining suggests a pelvic floor problem. Abdominal pain alongside it raises the possibility of irritable bowel syndrome.
First-line treatment
For most patients treatment starts with diet, adequate fluid and fibre. Fibre supplementation is a gentler first step than laxatives and in older adults has allowed a majority to stop laxatives altogether. Where medicines are needed, osmotic agents come first. Polyethylene glycol outperforms lactulose for stool frequency, stool consistency, abdominal pain and need for rescue medication, and magnesium salts such as magnesium oxide are comparably effective, so osmotic laxatives — PEG and magnesium — are the recommended first-line drugs.
Stimulant laxatives such as bisacodyl are reserved for rescue or second-line use rather than being the starting point.
When first-line treatment fails
The commonest reason for medically refractory chronic constipation is a defaecatory disorder, which may be structural, functional or both. Once diet, fibre and osmotic laxatives have failed, the next step is physiological assessment of the outlet rather than escalation of laxatives.
Testing may include anorectal physiology studies and dynamic imaging — defaecography by fluoroscopy or MRI, or dynamic ultrasound — to distinguish functional from structural causes and to identify a rectocele, intussusception or non-relaxing puborectalis.
Specific therapies for pelvic floor dysfunction
For outlet obstruction caused by failure of the puborectalis to relax, injection of botulinum toxin into the puborectalis and external sphincter can be considered, though the benefit is often temporary and may wane within about three months.
Biofeedback improves rectal sensitivity and compliance and is first-line therapy for symptomatic pelvic floor dyssynergia. It requires an engaged patient, an individually designed programme, and periodic top-up sessions to maintain benefit.
Surgery
Surgery is a last step and is preceded by colonic transit testing — radio-opaque markers, scintigraphy or a wireless motility capsule — because the operation depends on the mechanism.
For patients with significant outlet obstruction from a rectocele, repair can be considered once any coexisting functional problem such as non-relaxing puborectalis has been addressed. For severe obstructed defaecation from rectal intussusception unresponsive to conservative treatment, repair surgery may help. For isolated refractory slow-transit constipation, total colectomy with ileorectal anastomosis is an option. Stapled transanal rectal resection is not recommended for rectocele or intussusception because of its complication rate, and a permanent stoma is the final option for otherwise refractory disease.
Practical summary
The sequence is: exclude structural disease, classify the subtype, treat with fibre and osmotic laxatives, test the outlet if that fails, and use pelvic floor therapy before anyone mentions surgery.
Sources and further reading
One reference to a U.S. government health source (National Institutes of Health or MedlinePlus) for the medical background of this guide. It is context, not a substitute for advice from your treating doctor.
General information for international patients, not medical advice or a diagnosis. Read the medical disclaimer.